



Erectile dysfunction is one of the most common unstated reasons couples move toward a cuckold or hotwife dynamic, and the community forums are full of men saying so directly. It can work, but only when the ED is medically investigated first rather than routed around, because ED is a documented early warning sign of cardiovascular disease — the American Heart Association journal Circulation reports that it typically appears three to five years before a heart attack.
Key Takeaways
- Get the medical workup before the relationship conversation. ED precedes a first cardiovascular event by roughly three years, and treating the kink as the solution can mean ignoring a vascular warning.
- The numbers are ordinary, not shameful. The NIDDK estimates 30 to 50 million American men have ED, affecting about 40% at age 40 and 70% by age 70.
- Opening a marriage does not reliably fix ED and sometimes worsens it. Pyke’s 2020 review found sexual performance anxiety affects 9% to 25% of men and directly drives psychogenic ED.
- Consent is the failure point. If she agrees mainly to solve his medical problem, that is accommodation rather than desire, and it tends to collapse within a year.
- ED that is situational — present with a partner, absent otherwise — points toward psychogenic causes and responds to different treatment than vascular ED does.
Ask on any cuckold forum whether sexual dysfunction played a role and the thread fills fast. A September 2025 thread on r/CuckoldPsychology asking whether members agreed to be cuckolded because of impotence or weak erections drew extensive discussion. The Our Hotwives forum runs a long-standing thread on the same question. FabSwingers has one. Cuckold Marriage Info has a dedicated discussion on erection problems during threesomes. On polyamory.com, a thread titled “Opening our marriage due to ED issues” lays out the reasoning in the title alone.
What almost none of those conversations include is a doctor. That gap is the reason this article exists, because the medical facts change what the right decision looks like.
How common is erectile dysfunction, actually?
Common enough that treating it as a personal failing is statistically absurd. The National Institute of Diabetes and Digestive and Kidney Diseases estimates that between 30 million and 50 million men in the United States have ED, and reports that about 40% of men are affected at age 40, rising to 70% by age 70.
The foundational dataset is the Massachusetts Male Aging Study, which surveyed 1,709 men aged 40 to 70 between 1987 and 1989. Feldman and colleagues published the results in 1994 and found a combined prevalence of 52% — broken down as 17% minimal, 25% moderate and 10% complete.
More recent national data from Selvin and colleagues, published in the American Journal of Medicine in 2007 using NHANES survey data, put overall US prevalence at 18%, or roughly 18 million men, with a steep age gradient: 5.1% among men aged 20 to 39 against 70.2% among men aged 70 and over. Among men with diabetes, prevalence was 51.3%.
| Source | Population | Finding |
|---|---|---|
| NIDDK | US men, all ages | 30–50 million affected; about 40% at age 40, 70% by age 70 |
| Massachusetts Male Aging Study (Feldman et al., 1994) | 1,709 men aged 40–70 | 52% combined prevalence: 17% minimal, 25% moderate, 10% complete |
| Selvin et al., 2007, NHANES | US men aged 20+ | 18% overall; 5.1% at 20–39, rising to 70.2% at 70+ |
| Johannes et al., 2000 | Men aged 40–69 | About 26 new cases per 1,000 men each year, rising with diabetes, heart disease and hypertension |
| Pyke, 2020, Sexual Medicine Reviews | Review of sexual performance anxiety | Affects 9–25% of men and contributes directly to psychogenic ED |
One line from the NIDDK deserves repeating because it contradicts what most men assume: ED is more likely as you get older, but it is not a routine part of aging. It is a symptom, and symptoms have causes worth identifying.
Why does ED push couples toward cuckolding?
Three distinct routes show up in the community accounts, and they have very different outcomes.
The first is practical. One partner’s capacity for intercourse has changed and the other’s desire has not. Rather than accept a sexless marriage or a betrayal, the couple restructures the arrangement so her sex life continues with his knowledge and agreement. This is the version that reads most clearly in the forum threads, and it is the version most likely to work.

The second is psychological, and it runs the other direction. Some men find that the scenario itself produces arousal that ordinary sex no longer does. Threads on recovery forums describe men who can maintain an erection to cuckold material while struggling with partnered sex — which is a meaningfully different problem, and one that points toward conditioned response rather than a vascular issue.
The third is avoidance, and it is the one to watch for. Here the dynamic functions as a way to never have the medical conversation, never see a urologist, and never test whether the problem is treatable. The kink becomes a permanent workaround for something that was often fixable. Every clinician-facing description of ED treatment starts from the position that most cases respond to something — medication, vascular treatment, hormone correction, therapy, or a medication change.
Distinguishing which of the three you are in matters more than any rule you write down. If the honest answer is the third one, the relationship structure is not the thing that needs attention first.
What is ED actually telling you about your heart?
This is the section most likely to matter to a reader’s actual life, and it almost never appears in lifestyle writing on this subject.
The arteries that supply the penis are narrower than the coronary arteries. Mayo Clinic explains the consequence plainly: because those vessels are smaller, arterial damage tends to show up there first, which means ED can appear years before any cardiac symptom. Johns Hopkins Medicine describes the same mechanism, noting that arterial damage surfaces in the smaller vessels “often years ahead of heart disease symptoms.”
The timeline has been quantified. A review in Circulation, the American Heart Association journal, states that erectile dysfunction usually comes three to five years before a heart attack, and frames that interval as an opportunity — time in which atherosclerosis can be treated and an event potentially prevented. A 2021 review in the same literature estimates ED precedes a first cardiovascular event by around three years. Raheem and colleagues, writing in 2016, described ED as a sentinel marker of subclinical cardiovascular disease that likely precedes symptomatic coronary artery disease.
Put in the terms this audience needs: a man who develops ED in his forties or fifties and responds by restructuring his marriage instead of seeing a doctor may be trading a treatable warning for an untreated one. The risk factor list overlaps almost completely — diabetes, heart disease, obesity, hypertension, and the medications used to manage them all appear on both sides. Johannes and colleagues found in 2000 that ED incidence rose specifically with diabetes, heart disease and hypertension.
The instruction is simple and it is not negotiable: book the appointment first. Whatever you decide about the relationship afterward is a separate question, and it will be a better-informed one.
Does opening a marriage fix erectile dysfunction?
Sometimes, partially, and often not in the way couples expect.
Where it helps, the mechanism is usually pressure reduction. If a man’s ED is driven substantially by performance anxiety, removing the obligation to perform can break the feedback loop. Pyke’s 2020 review in Sexual Medicine Reviews found that sexual performance anxiety affects 9% to 25% of men and contributes directly to psychogenic ED, and 6% to 16% of women. Rowland’s 2019 work describes the mechanism: people with performance anxiety focus heavily on themselves and their own functioning rather than on the sexual cues their partner is giving, which reliably makes the problem worse. A structure in which he is not the one expected to perform can genuinely interrupt that.
Where it fails, the same anxiety simply relocates. Adding a third person to a situation a man already finds high-stakes raises the stakes rather than lowering them. The Cuckold Marriage Info discussion on erection difficulties during threesomes is exactly this: men who were functional alone with their wives and were not once a second man was present. If the plan involves him participating, the anxiety load goes up, not down.
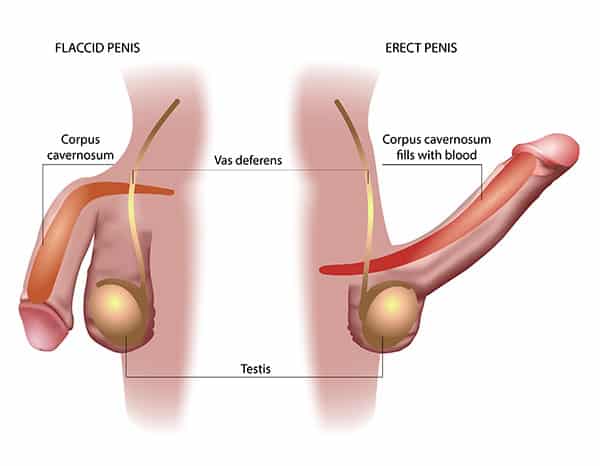
There is also a category error worth naming. If the ED is vascular — the most common cause in men over 45 — no relationship structure will affect it. Novelty can temporarily mask vascular ED because acute arousal recruits more blood flow, which produces a short-lived improvement that couples sometimes read as a cure. It is not one. The underlying arterial problem is unchanged and still progressing.
Where does consent break down in ED-driven arrangements?
This is the failure mode I hear about most in follow-up mail, and it is structural rather than personal.
When a couple opens up because of ED, the framing is almost always his problem, her solution. He raises it, he explains the reasoning, and she agrees. On paper that is consent. In practice it is frequently accommodation — she is solving a problem for him rather than pursuing something she wants, which is a different thing and behaves differently over time.
Accommodation-based arrangements tend to degrade in one of two directions. Either she finds she does want it, at which point the couple is in a real dynamic and has to renegotiate rules written for a different situation. Or she does not, resentment accumulates on both sides, and the arrangement ends badly with the ED still untreated. The distinction between agreement and desire is the same line I drew in where consent ends and betrayal begins, and ED-driven openings sit right on top of it.
There is a mirror-image version. Some men agree to a dynamic they do not want because they feel their ED has cost them standing — that they owe her this. That is not consent either. It is guilt with a rulebook attached, and it produces the anxiety spiral I covered in cuck angst.
The test is uncomfortable but clarifying. Ask whether either of you would still want this arrangement if the ED were cured tomorrow. If the honest answer from either side is no, you are building a relationship structure on a medical symptom, and the structure will only last as long as the symptom does.
What do couples who handle this well actually do?
The pattern across the accounts that end well is consistent, and it is a sequence rather than a set of rules.
They see a doctor first and get an actual diagnosis — vascular, hormonal, neurological, medication-related, psychogenic, or some combination. That single step determines everything downstream, because situational ED and vascular ED are different problems with different treatments. ED that is absent alone but present with a partner points toward the psychogenic end; ED that is constant regardless of context points toward the vascular end.
They separate the two decisions. Treating the ED and opening the marriage are independent choices, and couples who make them together usually cannot tell afterward which one changed anything. Treat first, wait, then decide about the relationship with a clearer baseline.
They define his role explicitly rather than defaulting to one. A man whose ED is anxiety-driven and who plans to be in the room has arranged for the anxiety to be worse. The distinctions between the stag, cuckold and bull roles are practical here, not semantic — they describe different levels of presence and different demands on him.
They bring in a professional when the conversation stalls. A urologist handles the mechanism; a kink-aware therapist handles the relationship. Our guide to finding a kink-aware therapist covers how to find someone who will not treat the dynamic itself as the presenting problem.
And they pace it around the body they actually have. The health-planning approach in our guide to how couples over 40 start applies directly: plan for physical change in advance rather than discovering it mid-encounter.
Doctor or therapist: which do you need?
| What you are seeing | Points toward | Start with |
|---|---|---|
| Gradual onset over months or years, present in every context | Vascular or hormonal | Primary care or urologist, plus cardiovascular screening |
| Sudden onset tied to a new medication | Medication side effect | Prescribing doctor — do not stop the medication yourself |
| Fine alone, unreliable with a partner | Psychogenic or performance anxiety | Sex therapist or CBT-trained clinician |
| Fine in the fantasy, unreliable in practice | Conditioned response | Kink-aware sex therapist |
| Function is fine; the conflict is about the arrangement | Relationship, not medical | Kink-aware couples therapist |
| ED plus diabetes, hypertension or known heart risk | Cardiovascular | Doctor, promptly — this is the sentinel-marker case |
Frequently asked questions
It is one of the most frequently cited reasons in community discussion. Dedicated threads on r/CuckoldPsychology, Our Hotwives, FabSwingers and polyamory.com all ask whether sexual dysfunction drove the decision, and all draw substantial responses. No formal prevalence study has measured it.
Yes, and this is well established. The arteries supplying the penis are narrower than the coronary arteries, so damage appears there first. Circulation reports that ED usually precedes a heart attack by three to five years, which is why a new onset warrants medical assessment rather than a workaround.
Not reliably. It can help when performance anxiety is the main driver, since Pyke’s 2020 review links that anxiety directly to psychogenic ED. It will not affect vascular ED, and adding a third person often increases performance pressure rather than reducing it.
Context is the clearest signal. ED that is constant in every situation points toward vascular, hormonal or medication causes. ED that appears only with a partner while function is normal otherwise points toward psychogenic causes. A doctor can confirm the distinction properly.
Not in itself, provided both partners genuinely want the arrangement and the ED has been medically assessed. It becomes a problem when one partner is accommodating rather than choosing, or when the dynamic is being used to avoid a diagnosis that could be treated.
The short version
Erectile dysfunction pushes a meaningful number of couples toward cuckolding and hotwifing, and for some of them the arrangement is a genuine improvement on the alternatives. What separates the couples it works for from the couples it damages is almost always sequence: diagnosis first, relationship decision second, with both partners answering honestly whether they would still want this if the ED resolved. ED is a treatable symptom and a documented cardiovascular warning, and a relationship structure is not a substitute for either the treatment or the warning. Handle the medicine, then decide what you want — in that order.
Sources
- National Institute of Diabetes and Digestive and Kidney Diseases — “Definition & Facts for Erectile Dysfunction.” https://www.niddk.nih.gov/health-information/urologic-diseases/erectile-dysfunction/definition-facts
- Feldman HA et al. — “Impotence and its medical and psychosocial correlates: results of the Massachusetts Male Aging Study,” Journal of Urology, 1994. https://pubmed.ncbi.nlm.nih.gov/8254833/
- Selvin E et al. — “Prevalence and Risk Factors for Erectile Dysfunction in the US,” American Journal of Medicine, 2007. https://www.amjmed.com/article/S0002-9343(06)00689-9/fulltext
- Johannes CB et al. — “Incidence of erectile dysfunction in men 40 to 69 years old,” Journal of Urology, 2000. https://pubmed.ncbi.nlm.nih.gov/10647654/
- American Heart Association — “Cardiovascular Implications of Erectile Dysfunction,” Circulation. https://www.ahajournals.org/doi/10.1161/circulationaha.110.017681
- Mayo Clinic — “Erectile dysfunction: A sign of heart disease?” https://www.mayoclinic.org/diseases-conditions/erectile-dysfunction/in-depth/erectile-dysfunction/art-20045141
- Johns Hopkins Medicine — “Special Heart Risks for Men.” https://www.hopkinsmedicine.org/health/wellness-and-prevention/special-heart-risks-for-men
- Raheem OA et al. — “The Association of Erectile Dysfunction and Cardiovascular Disease,” 2016. https://pmc.ncbi.nlm.nih.gov/articles/PMC5675247/
- Pyke RE — “Sexual Performance Anxiety,” Sexual Medicine Reviews, 8(2), 2020. https://pubmed.ncbi.nlm.nih.gov/31447414/
- Rowland DL — “Anxiety and Performance in Sex, Sport, and Stage,” 2019. https://pmc.ncbi.nlm.nih.gov/articles/PMC6646850/
- r/CuckoldPsychology — “Do some cuckolds have sexual problems? Impotence, soft erections,” September 2025. https://www.reddit.com/r/CuckoldPsychology/comments/1n6eufa/do_some_cuckolds_have_sexual_problems_impotence/
- Our Hotwives forum — “Did sexual dysfunction play a role in turning you cuckold?” https://ourhotwives.org/forum/viewtopic.php?t=37592

